
Clinician drug monograph • Last reviewed: 20 September 2026
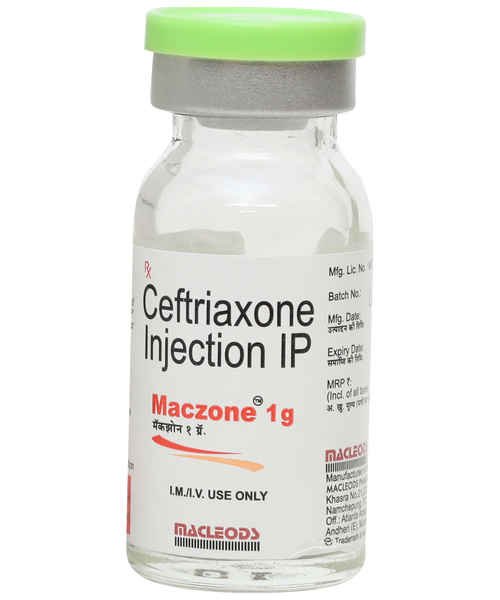
Ceftriaxone is a third-generation cephalosporin supplied as powder for IV or IM use. Use only for susceptible bacterial infections and follow the actual product label, antimicrobial policy and culture data.
Verified dosage form and India caveat
This guide focuses on the powder-for-injection vial. Indian listings include 1 g vials; other brands and strengths exist. Verify the vial label, diluent, final concentration and route before preparation.
Labelled dose framework
- Adults: usual labelled range 1–2 g once daily or in equally divided doses twice daily depending on infection; maximum 4 g/day.
- Paediatric patients: labelled dosing is indication- and weight-dependent. For many serious infections other than meningitis, 50–75 mg/kg/day in divided doses every 12 hours is described, maximum 2 g/day. Meningitis uses a higher label-directed regimen and must be checked directly.
- Neonates: special restrictions apply. Ceftriaxone is contraindicated in hyperbilirubinaemic neonates and in neonates requiring calcium-containing IV solutions.
Educational calculation: for a prescribed 50 mg/kg dose in a 20 kg child, dose = 50 × 20 = 1,000 mg. This demonstrates arithmetic only; the indication, interval and maximum must be independently verified.
Reconstitution, dilution and administration
Reconstitution volumes and resulting concentrations differ by vial size, manufacturer and IV versus IM route. Use only the exact package insert for the vial in hand. For IV infusion, compatible diluent and infusion time must be checked; do not use calcium-containing diluents such as Ringer’s or Hartmann’s to reconstitute ceftriaxone. Never mix or simultaneously administer ceftriaxone with calcium-containing IV solutions through the same line.
Storage and stability
Unopened and reconstituted storage limits depend on the manufacturer, concentration and diluent. Record preparation time and beyond-use time from the actual label/local pharmacy policy; discard discoloured, particulate or out-of-window solution.
Renal/hepatic considerations
Usual doses often need no adjustment in renal failure alone, but combined significant renal and hepatic dysfunction requires close clinical and concentration-aware review. Do not exceed label limits without specialist oversight.
Pregnancy and lactation
Use in pregnancy or breastfeeding requires patient-specific benefit–risk assessment and current label review. Ceftriaxone can cross the placenta and is excreted in human milk in low concentrations.
Contraindications, interactions and warnings
- Serious immediate hypersensitivity to ceftriaxone/cephalosporins.
- Neonatal bilirubin displacement and calcium–ceftriaxone precipitation warnings.
- C. difficile-associated diarrhoea, haemolytic anaemia, biliary sludge/pseudolithiasis, pancreatitis and seizures are important serious risks.
- Check anticoagulants and other nephrotoxic/interaction-prone therapies against a current interaction resource.
Monitoring
Clinical response, cultures, allergy, bowel symptoms, CBC, renal/hepatic function when prolonged or high risk, and line/IM-site complications. Escalate suspected anaphylaxis or haemolysis immediately.
Primary sources
Medication-error warning: check brand concentration, route, diluent, calcium exposure and local protocol before preparation and administration.
Medical disclaimer: Professional education only; not an individual prescription or substitute for the current approved label, antibiogram, pharmacist review or local protocol.